
Perimenopause and bleeding after intercourse usually have a dull explanation: a cervical ectropion, a small polyp, or tissue thinned by falling oestrogen. Most episodes settle on their own. No guideline, though, lets anyone sort the dull causes from the serious ones without looking, so the cervix gets examined, whatever your last screening result said.
Listen to this article, about 12 minutes. A synthetic voice reads the article and announces each section title as it begins; tables are read row by row and the questions at the end are left out.
Recorded 18 October 2026 from the article as published that day. Press a chapter to jump there; the highlighted line is what is playing. A play button sits beside every section heading, and once you scroll past this player a bar at the bottom of the screen keeps the controls in reach. Tap or click any sentence to hear the reading start from there.
On this page: the dull causes that explain most bleeding after sex in your forties, the published cancer figures with their denominators, the one sentence in NICE guideline NG12 that puts the examination before the symptom, why a clear smear does not skip it, and the twelve month line that perimenopause blurs.
Think you already know this? Five questions, one minute.
Every answer is on this page. Answer from what you know now; the page fills in the rest.
-
1. Which is described in the 2014 review as the most common benign growth on the cervix?
Per Tarney and Han, 2014; they bleed easily because they are friable, and the same review is explicit that ectropion is not a pathological condition. Read the section
-
2. Among UK women referred on the two week wait for bleeding after sex or an abnormal looking cervix, how many had cervical cancer in the 2022 cohort?
Per Jasper and colleagues, 2022: none among the 492 women up to date with screening, in a single retrospective cohort with seven cancers in total, so the subgroup figures rest on very few cases. Read the section
-
3. What triggers a suspected cancer pathway referral in the cervical recommendation of NICE guideline NG12?
Per NG12; every operative word in that sentence sits after the words on examination, which is the one step the reassuring pages skip. Read the section
-
4. What does the national cervical screening leaflet say screening is not?
Per the NHS leaflet, which lists bleeding during or after sex among the symptoms it is important to get checked by a GP; screening cannot see a polyp, an ectropion or thinned tissue. Read the section
-
5. What is the dividing line between postcoital bleeding and postmenopausal bleeding?
Perimenopause makes that line hard to use, because periods can stay regular while everything else changes, and a hormonal coil or the pill stops the clock being read at all. Read the section
What usually causes bleeding after sex in your forties?
The list is longer and duller than the search results suggest. A 2014 review by Tarney and Han, Obstetrics and Gynecology International, 2014 sets out the usual suspects: cervical ectropion, cervical and endometrial polyps, cervicitis, vaginal atrophy, trauma, and, much less often, cervical, vaginal or endometrial cancer. Polyps are described there as the most common benign growth on the cervix, at an incidence of 4% of gynaecology patients, and they bleed easily because they are friable. Ectropion is columnar tissue from inside the cervical canal sitting on the outside, where the vaginal environment is rougher on it than it was built for. The same review is explicit that ectropion is not a pathological condition.
Perimenopause adds its own contribution. Falling oestrogen thins the tissue of the vagina and cervix, which is a large part of why bleeding after sex starts appearing in the forties in people who never had it before. It is also why almost every commercial page on this topic arrives, by paragraph four, at a moisturiser it happens to sell. The tissue explanation is frequently the right one. The problem is that frequently right is not a category anyone can apply to themselves from the sofa, and the thin tissue and the polyp produce exactly the same spot of blood.
How often does bleeding after sex turn out to be cancer?
Rarely, and there are published numbers rather than reassurance. Here is what the three most useful studies actually measured, with the figure and the source on every row.
| What was measured | The number | Source |
|---|---|---|
| Two year cumulative incidence of bleeding after sex, women aged 40 to 54 | 7.7% (95% CI 6.2 to 9.5), in 2,104 naturally menstruating women | Shapley and colleagues, BJOG, 2013 |
| Episodes that stopped and did not come back over two years | 51% (95% CI 40 to 62) | Shapley and colleagues, BJOG, 2013 |
| Cancers among the 785 women in that cohort who reported bleeding between periods or after sex | One uterine cancer | Shapley and colleagues, BJOG, 2013 |
| Cervical cancer among UK women referred on the two week wait for bleeding after sex or a cervix that looked abnormal | 7 of 604, or 1.16% | Jasper and colleagues, Journal of Obstetrics and Gynaecology Research, 2022 |
| Positive predictive value of bleeding after sex on its own | 1.70% (95% CI 0.64 to 3.7) | Jasper and colleagues, Journal of Obstetrics and Gynaecology Research, 2022 |
| Cervical cancer among the 492 of those women who were up to date with screening | None | Jasper and colleagues, Journal of Obstetrics and Gynaecology Research, 2022 |
| Cervical cancer among those out of date with screening or outside the screening age range | 6.25% (p below 0.001) | Jasper and colleagues, Journal of Obstetrics and Gynaecology Research, 2022 |
| CIN 2 or worse among 411 women with bleeding after sex sent for colposcopy in Israel | 3 women, or 0.7% | Cohen and colleagues, PLOS ONE, 2019 |
| Odds of CIN 1 or worse with bleeding after sex compared with without | Odds ratio 1.82 (95% CI 1.02 to 3.33) | Cohen and colleagues, PLOS ONE, 2019 |
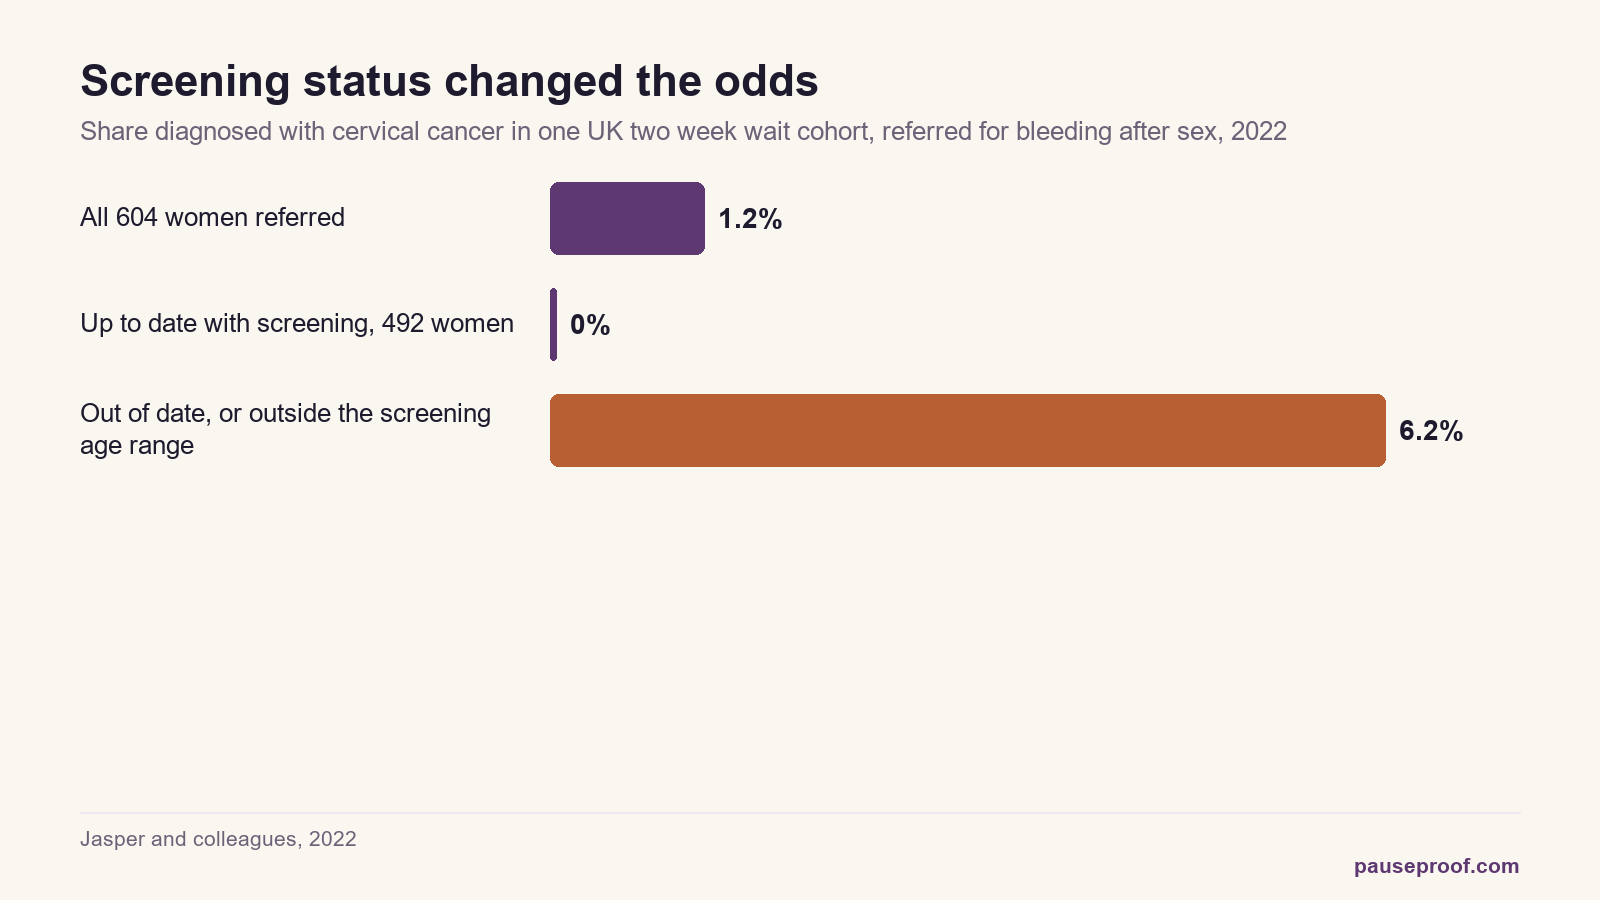
Read the table honestly and it says two things at once. Roughly one in a hundred women referred with this symptom in the UK cohort had cervical cancer, which is small. It is not zero. And the row that deserves the most attention is the screening one: in that cohort no cancer was found among the women who were up to date with screening, while 6.25% of those who were out of date, or past the age when invitations stop, were diagnosed.
Two caveats belong with those figures. Jasper and colleagues, Journal of Obstetrics and Gynaecology Research, 2022 is a single retrospective cohort from one UK service with seven cancers in total, so the subgroup percentages rest on very few cases and should not be read as precise. Cohen and colleagues, PLOS ONE, 2019 studied women already sent for colposcopy in Israel, a group selected before the study started, so its rates do not transfer to everyone who notices spotting once.
What does the guidance actually tell a doctor to do?
This is where the ranking pages and the guideline part company. NICE guideline NG12, the suspected cancer guideline, contains no standalone recommendation to refer someone because they have bled after sex. Its cervical recommendation, numbered 1.5.13 in the guideline text carried on the NIH Bookshelf and dated 2015 within a guideline NICE lists as last updated on 15 April 2026, reads: “Consider a suspected cancer pathway referral for women if, on examination, the appearance of their cervix is consistent with cervical cancer.”
Every operative word in that sentence sits after “on examination”. The trigger is not the symptom, it is what somebody sees. Which means the pages that stop at “it is probably just dryness” are skipping the only step the guideline specifies. They are not wrong about the likely cause. They are quietly removing the thing that establishes it.

The contrast with postmenopausal bleeding is deliberate. In the same guideline, recommendations 1.5.10 and 1.5.11 make the symptom itself the trigger: a suspected cancer pathway referral for unexplained bleeding more than twelve months after periods stopped in women aged 55 and over, and consideration of the same referral under 55. We covered that pathway separately in why even spotting after the menopause gets checked. Bleeding after sex is routed through the examination instead. Different symptom, different door, same building. One caution on those numbers: the April 2026 update to NG12 dealt with unscheduled bleeding while taking HRT and endometrial cancer referral, and on 18 October 2026 we could not confirm whether it renumbered or reworded 1.5.10 and 1.5.11, so check the current text before quoting them. If what you are seeing is light spotting between periods rather than bleeding after sex, our page on why perimenopause spotting is common but still worth a check covers that question.
Does a clear smear mean the examination can be skipped?
No, and the reason is stated by the programme itself. The NHS cervical screening leaflet, updated on 23 March 2026, says screening “is not a check for other cancers of the reproductive system, such as ovary, womb, vulval or vaginal cancer”, and lists bleeding during or after sex among the symptoms of cervical cancer that it is important to get checked by a GP. Screening in England is offered to women aged 25 to 64 every five years. It tests a sample for HPV. It does not look for a polyp, it cannot see an ectropion, and it has nothing to say about thinned tissue.
There is a genuine tension here worth naming rather than smoothing over. The UK cohort above found no cervical cancers at all among women who were up to date with screening, which is a real piece of reassurance. What does not follow is that the examination was pointless for them: every woman in that cohort had already been examined and referred, which is how the polyps, the ectropions and the infections got identified and treated. Screening status shifts the odds. It does not answer the question of what is bleeding.
One detail matters more for this site’s readers than for most. The women in that 6.25% group were out of date with screening or outside the screening age range, and in England invitations stop at 64. If your bleeding starts in your fifties and your last invitation is some years behind you, you are closer to that group than to the reassuring one.
How is this different from bleeding after the menopause?
The dividing line is twelve months. Bleeding more than twelve months after your last period is postmenopausal bleeding and has its own pathway. Bleeding after sex while periods are still happening, however erratically, is postcoital bleeding and has the one described above.
Perimenopause makes that line hard to use, which is the honest difficulty here. Periods can stay stubbornly regular while everything else changes, so the twelve month clock never starts. And if you have no periods to count because of a hormonal coil or the pill, the clock cannot be read at all. In that situation the date of the bleeding and what else was going on around it carry more weight than the calendar, which is the sort of thing a symptom diary is actually good for.

What tends to happen at the appointment?
An examination of the vulva, vagina and cervix with a speculum, which takes a couple of minutes and is the whole point of the visit. Swabs for infection where the history suggests them: the 2014 review names chlamydia, gonorrhoea and trichomonas among the organisms behind cervicitis. A cervical screening test only if one is due or overdue, rather than an extra one added because of the symptom. Local NHS referral pathways commonly state that last point, though the underlying NICE clinical summary would not load for us on the day of writing, so treat it as commonly quoted rather than verified at source. And an onward referral if the cervix looks wrong.
Two things are written here without any jokes attached. Bleeding that is heavy, that comes with pain, or that keeps happening after several episodes is treated in the guidance as a reason to be seen rather than to wait and watch. And bleeding that starts more than twelve months after your last period is a separate matter with a separate pathway, whether or not sex was involved.
Before the appointment
The examination is the whole point of the visit, and these are the things that shape what happens around it. Tick each one once you have it written down.
What to bring, not a way of sorting the dull causes from the serious ones, which the guideline says needs an examination. Ticks are saved on this device only.
What has changed since this was first published?
- Corrected in October 2026: this page gave NG12’s last update as January 2026. NICE lists it as 15 April 2026, per the NG12 update information, when recommendations on unscheduled bleeding while taking HRT and endometrial cancer referral were added. The cervical recommendation quoted above, 1.5.13, was not part of that change as far as we could tell on 18 October 2026.
- Not rechecked on 18 October 2026: the exact wording and numbering of recommendations 1.5.10 and 1.5.11 after the April 2026 update. The NICE site refused our automated check, so treat those two numbers as the 2015 text.
Frequently asked questions
Is bleeding after sex ever just normal in perimenopause?
There is no threshold in the guidance below which it is defined as normal. It is common: in the cohort of 2,104 women aged 40 to 54, the two year cumulative incidence was 7.7%, and about half of the episodes stopped without recurring. Common and normal are not the same thing, and the examination is what separates them.
Can vaginal dryness on its own cause bleeding after sex?
Yes. Vaginal atrophy sits on the standard list of causes and thinning tissue is a real mechanism. It is also the first explanation most people reach for, which is the difficulty: at home it is indistinguishable from a cervical polyp or an ectropion, both of which bleed just as readily and neither of which responds to a moisturiser.
What if it only happened once?
A single episode still counts as postcoital bleeding and is still worth reporting. Writing down the date, whether there was any pain, how much bleeding there was and where you were in your cycle gives the appointment something concrete to work from, which matters more when cycles are irregular and dates blur together.
Will I automatically need a colposcopy?
Not from the symptom alone. In the Israeli series every woman had already been sent for colposcopy, and 0.7% of them had CIN 2 or worse. In the UK the referral trigger written into NG12 is the appearance of the cervix at examination, not the report of bleeding, so what happens next depends on what is seen.
Does spotting after sex mean perimenopause is further along?
No. The staging systems used to describe the transition do not use it as a marker at all. STRAW+10 stages the transition on changes in cycle length and on vasomotor symptoms, and carries nothing about bleeding after sex in either direction.
Could an infection be behind it?
It can. Cervicitis is on the list of causes, and chlamydia, gonorrhoea and trichomonas are named among the organisms responsible in the 2014 review. That is why swabs are often taken at the same appointment as the examination, and it is one of the causes with a straightforward resolution once identified.
Finished the page? The same five questions from the top, to see what stuck.
This article is general information, not medical advice, and is not a substitute for care from a qualified healthcare professional. Speak to your doctor about your own situation.

Leave a Reply